
How to Build a Real-World Evidence (RWE) Strategy for a Digital Health Product
Real-world evidence is now the currency of coverage decisions for digital health. Here is how to design an RWE strategy that regulators accept, payers cite, and your own team can actually run.
Most digital health teams discover real-world evidence the wrong way round. A payer asks what happens to their members after month six, a health system asks whether the effect holds outside the trial population, and the answer is a pilot deck with 40 engaged users. The trial is done, the product is live, and the data that would have answered the question was never structured to be analysed.
Real-world evidence is not a post-launch nicety. For digital health products it is often the primary evidence base, because the randomised trial you can afford is too short and too small to answer the questions buyers ask. Building the strategy early is cheaper than reconstructing it later.
What counts as real-world evidence
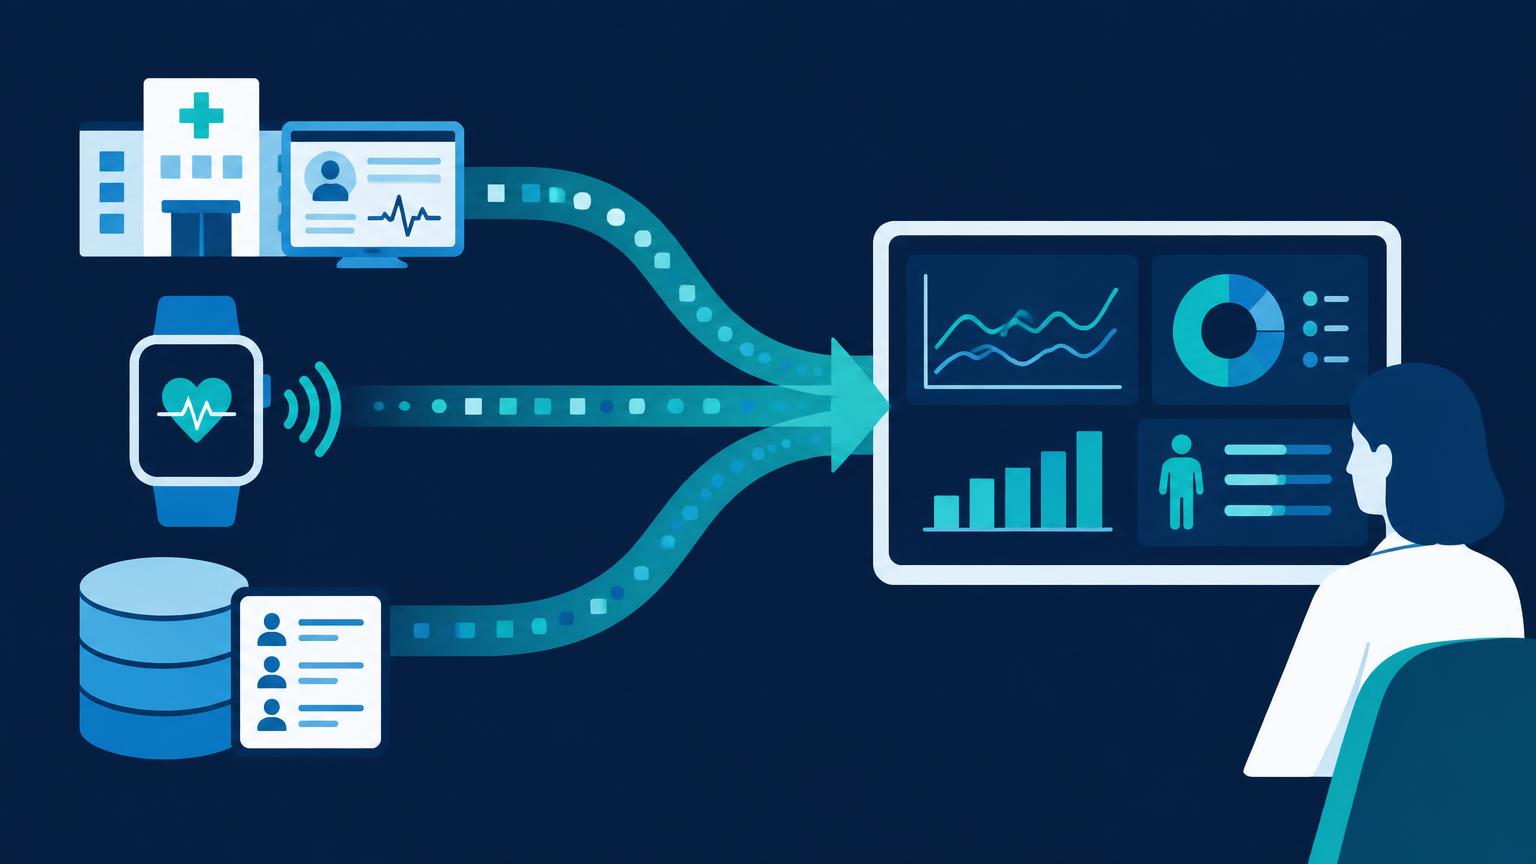
FDA draws a useful line between data and evidence. Real-world data is the raw material: electronic health records, claims and billing records, product and disease registries, patient-generated data from apps and wearables, pharmacy data. Real-world evidence is the clinical conclusion about benefit or risk derived from analysing that data. The FDA real-world evidence programme sets out that distinction and the agency's expectations for both.
For devices specifically, the guidance on the use of real-world evidence to support regulatory decision-making for medical devices is the document to read before designing anything. It explains what makes real-world data relevant and reliable enough to support a regulatory decision, and it is explicit that the bar is about data quality and fit for purpose, not about the label attached to the data source.
The reason this matters commercially is that the same data, gathered once and gathered properly, can serve three different audiences: a regulator considering an expanded indication, a payer deciding on coverage, and a health system deciding whether to renew.
Start from the decision, not the data
The most common failure is collecting everything and analysing nothing. An RWE strategy begins by naming the decisions it must influence, in order.
A regulatory decision might be support for a new indication, a change to your labelling, or postmarket evidence for a predetermined change control plan covering model updates. A coverage decision might be a commercial payer medical policy, a Medicare coverage determination, or a national assessment in Germany or France. A purchasing decision is the hospital value analysis committee asking what the contract does to their budget.
Each of those decisions has an evidence owner, a timetable and an accepted endpoint set. Write them down. Then work backwards: what would have to be true, measured in what population, over what horizon, compared against what alternative. That single exercise eliminates most of the data you were about to collect.
The five design choices that determine credibility
Population. Define eligibility the way a payer defines it, not the way your marketing defines it. If coverage will apply to adults with a confirmed diagnosis and a prior failed intervention, your evidence population should look like that, including the patients who disengage.
Comparator. This is where digital health studies most often collapse under review. Comparing against no intervention when a nurse-led programme already exists inflates the effect and invites rejection. Choose the real alternative in the care pathway, and be prepared to defend it.
Endpoint. Engagement is not an outcome. Choose clinical or utilisation endpoints that appear in payer policies: HbA1c, blood pressure control, avoided admissions, time to diagnosis, validated functional scores. If you use a patient-reported measure, use a validated one and know its minimum clinically important difference in advance.
Horizon. Chronic conditions are managed over years, and reviewers know it. Twelve weeks is a signal, not an answer. Plan for a follow-up window that matches the condition and the budget cycle of the buyer.
Confounding. Observational data carries selection effects. Say so, and address it with pre-specified methods: propensity matching, an external control arm, a difference-in-differences design against a comparable cohort. Pre-specification is what separates analysis from data dredging, and reviewers can tell the difference.
Data sources you can realistically use
Your own product telemetry is the cheapest and least persuasive on its own, because it captures use rather than outcome. It becomes powerful when linked to a clinical or claims source.
Electronic health record extracts from delivery partners give clinical outcomes, at the cost of a data use agreement and a lot of curation work. Claims data gives utilisation and cost, which is exactly what budget-holders want, but with a lag and no clinical granularity. Registries sit between the two, and for devices the coordinated registry approach promoted by the National Evaluation System for health Technology Coordinating Center is worth understanding before you build a bespoke one.
If your route runs through Medicare, read how CMS handles coverage with evidence development. It is the mechanism by which a technology gets paid for while the evidence is still being generated, and it is a legitimate strategy rather than a consolation prize.
Governance: the part that fails audits
Evidence generated from clinical data is a regulated record long before it is a marketing asset. Your pipeline needs versioned data sets, a documented analysis plan fixed before the data is unblinded, an audit trail for every transformation, and controlled access. If any of that touches a regulated submission, the 21 CFR Part 11 guide covers what an auditor will expect from your electronic records and signatures.
Privacy governance runs alongside it: lawful basis, minimisation, de-identification standard, and in Europe the interaction with post-market clinical follow-up obligations under EU MDR.
A twelve-month sequence that works
Months one to three: name the decisions, pick endpoints, draft the analysis plan, secure one data partnership. Months four to six: instrument the product to capture the endpoints, sign the data use agreement, run a feasibility pull on historical data. Months seven to nine: first interim analysis, internal only, to test whether the effect direction and size are plausible. Months ten to twelve: full analysis, manuscript or dossier, and a payer-facing summary written in the language of the market access audience rather than the clinical one.
Run the market side in parallel. Knowing which of the 25+ markets you are targeting, and what each one accepts as evidence, changes what you collect. MedTech Compass exists to make that comparison explicit rather than anecdotal.
The honest summary
An RWE strategy is not a study. It is a standing capability: defined questions, a governed data pipeline, pre-specified analysis, and a publication and dossier rhythm. Teams that build it early answer payer questions in weeks. Teams that do not spend two years explaining why their pilot is not generalisable.
Sources
- FDA — Real-World Evidence programme - FDA guidance — Use of Real-World Evidence to Support Regulatory Decision-Making for Medical Devices - National Evaluation System for health Technology Coordinating Center (NESTcc) - CMS — Coverage with Evidence Development - ISPOR — Good Practices reports for health economics and outcomes research - NICE — Health technology evaluations: the manual (PMG36)
This article is general information about evidence strategy, not regulatory or legal advice. Confirm requirements with the relevant regulator, payer or notified body before acting.
Follow MedTech Insights
New articles on FDA 510(k) and De Novo pathways, CE Mark and EU MDR, and device reimbursement — sent to your inbox as they publish.